Drug reference directory
Drug reference

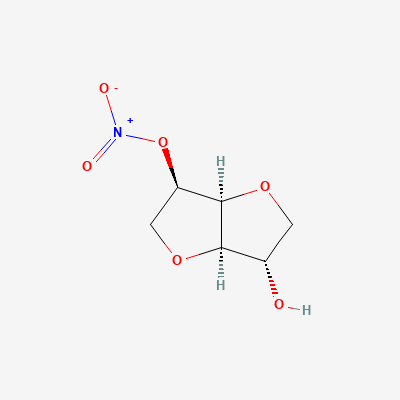
Isosorbide Mononitrate

Organic nitrate vasodilator · Antianginal

Also known as Isosorbide-5-mononitrate, ISMN
START
Check BP (ensure SBP >90). Verify no PDE5 inhibitor use in past 24-48h. Counsel on headache (common, usually resolves in 1 week).
TYPICAL MAX
240mg/day ER. Do not use TID/QID dosing (promotes tolerance). Maintain 10-12 hour nitrate-free interval daily.
STOP IF
SBP <90 mmHg, syncope, severe headache unresponsive to analgesia, methemoglobinemia (cyanosis, SpO2 discordance).
WATCH
Tolerance develops with continuous exposure—ensure 10-12 hour nitrate-free interval (asymmetric BID or morning-only ER). Headache is expected and usually transient. Hypotension risk increased with alcohol, other antihypertensives.
CDSCO approvedSchedule HJan AushadhiATC C01DA14
Dose laddermg/d
20start30ER start60titrate120ER higher dose240Max ER daily
Renal dose adjustmenteGFR mL/min/1.73m²
FULLNo adjustment needed15FULLNo adjustment ne…≥90

KDIGO 2024 + manufacturer label

Pharmacokineticsplasma · t hours
1hONSET4hPEAK5ht½12hDURATION
ONSET
1h · Onset 30-60 min (IR)
PEAK
4h · Tmax ER 3.5-5 hours
t½
5h · t½ ~5 hours
DURATION
12h · 12-24 hours (ER)
EXCRETION
Renal as metabolites (~96%)
route + CYP
INTERACTIONS
9 major
incl. contraindicated
PREGNANCY
Limited data; use only if clearly needed. Animal studies at high doses show adverse effects.
FDA category + note
Top interactionssee all 10 →
  • SildenafilContraindicatedTextbook-citedKDT 7e · p950
  • TadalafilContraindicatedTextbook-citedKDT 7e · p950
  • AvanafilContraindicatedDatabaseDDInter
  • Pde5 InhibitorsContraindicatedDatabaseKimi deep-research + Cla
Available in India

116 branded formulations and 18 fixed-dose combinations. Look up specific brands in the Drugs workspace.

Jan Aushadhi — generic available at GoI pharmacies

Mechanism

Converted to nitric oxide (NO) in vascular smooth muscle, activating guanylate cyclase → increased cGMP → dephosphorylation of myosin light chain → vasodilation. Preferentially dilates veins > arteries, reducing preload and myocardial oxygen demand.

Indications

Prevention of angina pectorisCongestive heart failure (adjunctive, with hydralazine—BiDil)

Dosing

Adult
Angina prophylaxis (IR): 20mg BID given 7 hours apart (asymmetric dosing to prevent tolerance). Angina prophylaxis (ER): 30-60mg daily in morning, may increase to 120mg daily; max 240mg/day (ER). Heart failure (BiDil): isosorbide dinitrate 20mg + hydralazine 37.5mg TID.
Pediatric
Not established in children.
Renal adjustment
No adjustment needed.
Hepatic adjustment
No adjustment needed; metabolized in liver but well-tolerated.
Geriatric
Start at 30mg ER daily; increased sensitivity to hypotension.
Max dose
240mg/day (ER); 40mg/day (IR BID)

Pharmacokinetics

Onset
IR: 30-60 minutes; ER: 1-2 hours
Peak effect
IR: Tmax 0.5-1 hour; ER: Tmax 3.5-5 hours
Duration
IR: 6-8 hours; ER: 12-24 hours
Half-life
~5 hours (IR and ER)
Bioavailability
~100% (no first-pass metabolism, unlike ISDN)
Protein binding
~5%
Metabolism
Hepatic denitration to isosorbide and sorbitol; glucuronidation
Excretion
~96% in urine as metabolites; ~2% unchanged

Contraindications

  • Hypersensitivity to nitrates
  • Severe hypotension (SBP <90 mmHg)
  • Cardiogenic shock
  • Sildenafil, tadalafil, or vardenafil use within 24-48 hours (PDE5 inhibitors)
  • Hypertrophic cardiomyopathy with outflow tract obstruction
  • Closed-angle glaucoma (relative)

Side effects

Common
Headache (most common—dose-dependent, often transient)DizzinessHypotensionTachycardia (reflex)Flushing
Serious
  • Severe hypotension / syncope
  • Reflex tachycardia (may worsen angina)
  • Methemoglobinemia (rare, high doses)
  • Nitrate tolerance (with continuous exposure)

Pregnancy & lactation

Pregnancy

Limited data; use only if clearly needed. Animal studies at high doses show adverse effects.

Lactation

Excretion in breast milk unknown; use with caution. No adverse effects reported in nursing infants.

Drug interactions

Sildenafil
Contraindicated
Textbook-cited

Precipitous and potentially fatal fall in blood pressure; myocardial ischemia

Concurrent use is absolutely contraindicated

Source: KDT 7e · p950

Tadalafil
Contraindicated
Textbook-cited

Precipitous and potentially fatal fall in blood pressure; myocardial ischemia

Concurrent use is absolutely contraindicated

Source: KDT 7e · p950

Avanafil
Contraindicated
Database

Profound and prolonged systemic hypotension, syncope, myocardial ischemia, and even death.

Concomitant use is absolutely contraindicated. A minimum of 12 hours should elapse between the last dose of avanafil and the administration of isosorbide mononitrate.

Source: DDInter

Pde5 Inhibitors
Contraindicated
Database

Potentiation of cGMP-mediated vasodilation → severe, potentially fatal hypotension.

Absolutely contraindicated. Sildenafil/vardenafil: avoid for 24h after nitrate. Tadalafil: avoid for 48h.

Source: Kimi deep-research + Cla

Riociguat
Contraindicated
Database

Riociguat (sGC stimulator) + nitrates → excessive hypotension.

Contraindicated. Use alternative antianginal if riociguat indicated.

Source: Kimi deep-research + Cla

Vardenafil
Contraindicated
Database

Profound and prolonged systemic hypotension, syncope, myocardial ischemia, and even death.

Concomitant use is absolutely contraindicated. A minimum of 24 hours should elapse between the last dose of vardenafil and the administration of isosorbide mononitrate.

Source: DDInter

Nitrous Acid
Severe
Database

Clinical effect not specified

Source: DDInter

Prilocaine
Severe
Database

Clinical effect not specified

Source: DDInter

Tizanidine
Severe
Database

Clinical effect not specified

Source: DDInter

Alcohol
Moderate
Database

Additive vasodilation and hypotension; may precipitate syncope.

Advise patient to avoid or minimize alcohol while taking nitrates.

Source: Kimi deep-research + Cla

2 additional unreviewed or low-confidence interactions hidden because their provenance or source detail is insufficient.

Related guidelines

Ask House about Isosorbide Mononitrate

Continue into a citation-backed clinical answer with the drug context already attached.

Textbook-sourced·Sources: KD Tripathi 7e, Katzung, BNF·Updated: 2026-05-19·Cockpit curated: 2026-05-19